
Why ACE Inhibitor Cough Can Persist
Written by: Waldrugmart Editorial Team
Reviewed by: Navdeep Singh, B.Pharm — Registered Pharmacist
Last reviewed:
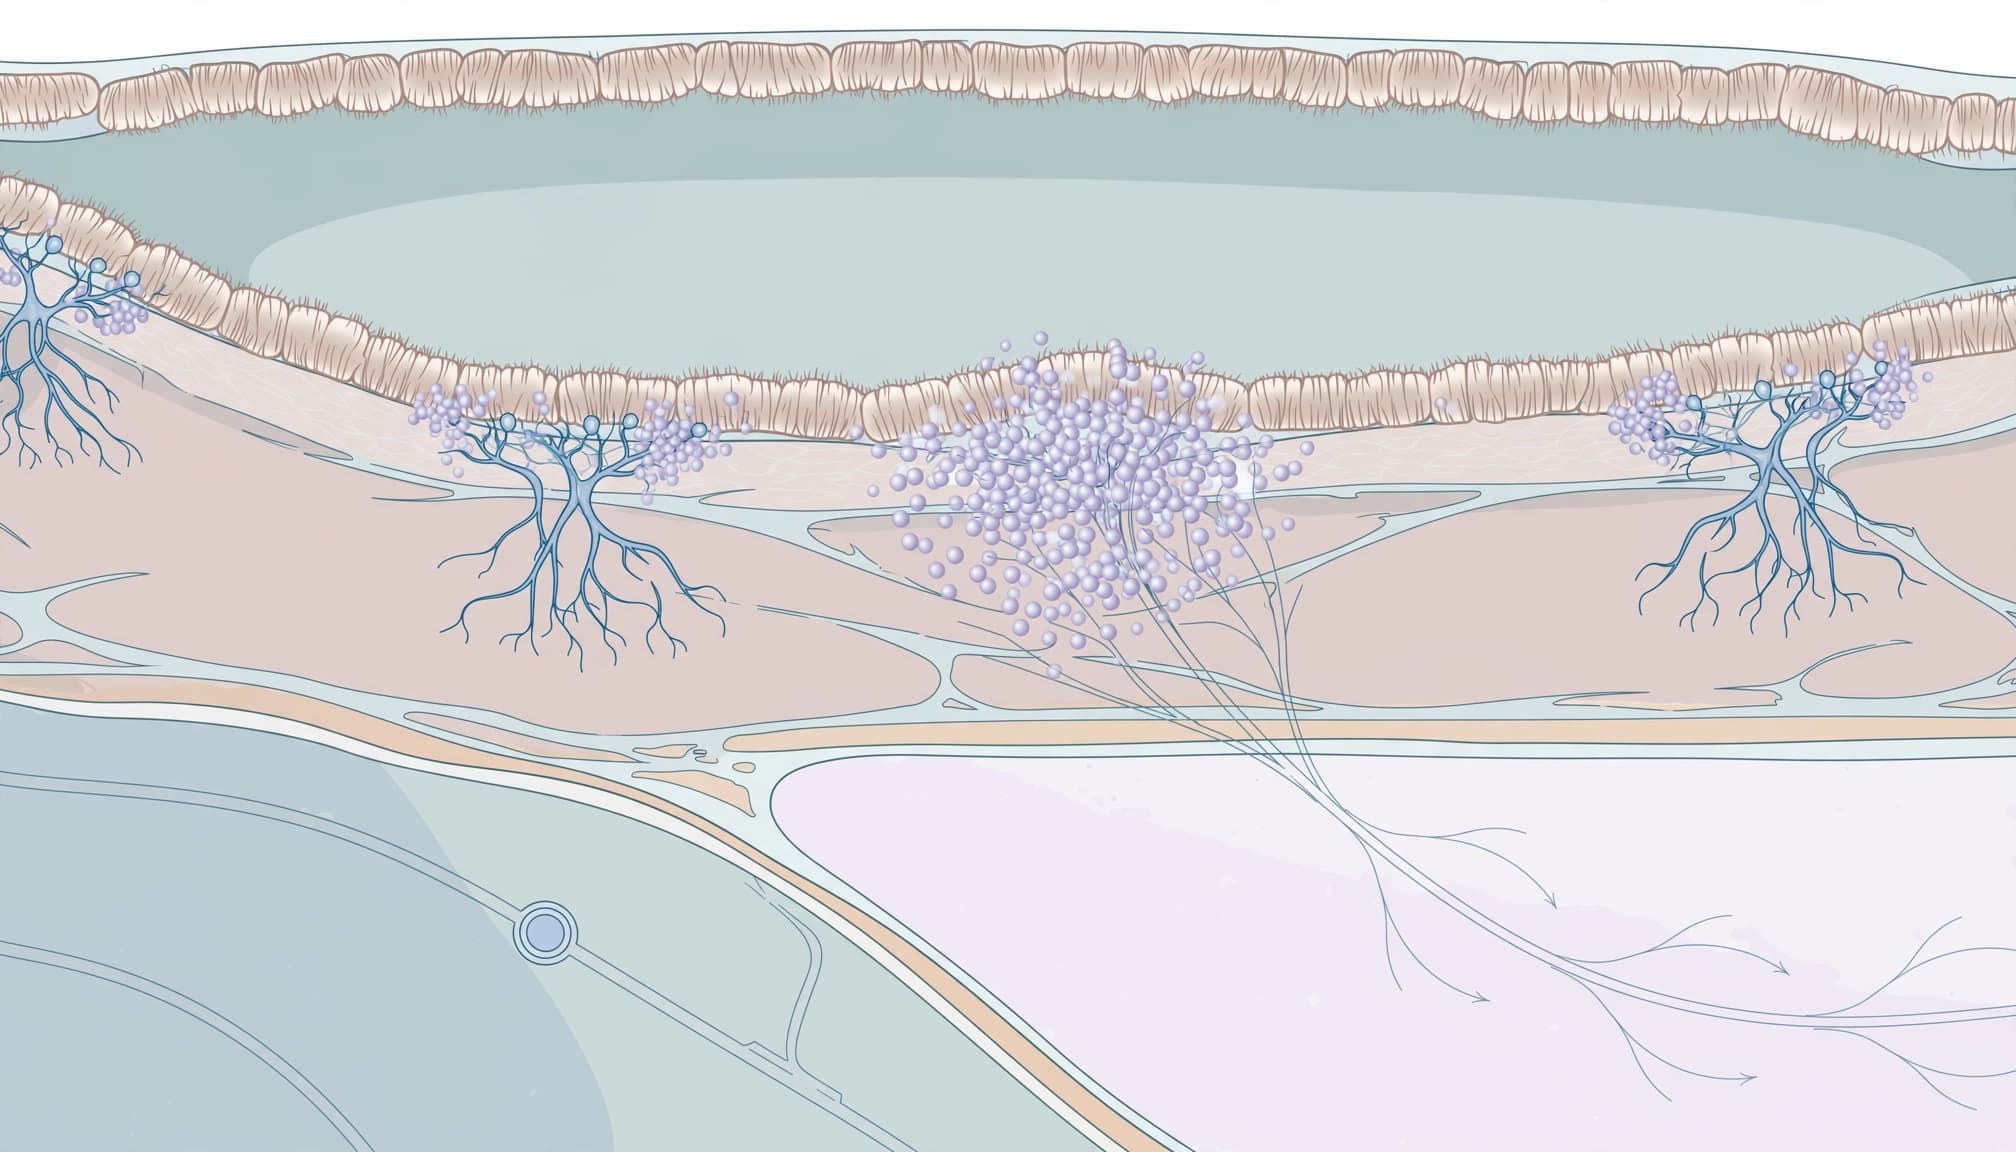
ACE inhibitor cough develops because these medicines slow the breakdown of bradykinin, a substance that can irritate airway nerves. The resulting cough is usually dry and tickly, and it can persist until a prescriber changes the treatment.
Medicines such as lisinopril protect the heart, kidneys, or circulation in selected patients, but coughing can disrupt sleep and daily life. Recognizing the pattern helps distinguish a manageable side effect from symptoms that need urgent assessment.
Table of contents
- Why the cough happens
- Symptoms and timing
- Medicines involved
- Switching treatment safely
- Other possible causes
- Emergency warning signs
- Costs and safe access
- Frequently asked questions
- The lasting distinction
Key takeaways
- Roughly one in ten patients develops a cough, although estimates vary across studies.
- A medicine taken without problems for months or years can still become a suspect.
- A prescriber-arranged switch to an ARB usually resolves the cough within several weeks.
- Lip, tongue, or throat swelling is a separate emergency, not an ordinary cough symptom.
Why ACE inhibitor cough happens
ACE stands for angiotensin converting enzyme. Blocking this enzyme lowers blood pressure, but it also changes how the body clears substances involved in coughing.
The blood-pressure pathway
The kidneys release renin, which converts angiotensinogen into angiotensin I. In the renin-angiotensin pathway, ACE then converts angiotensin I into angiotensin II.
Angiotensin II narrows blood vessels and promotes aldosterone release. Aldosterone increases sodium and water reabsorption by the kidneys. Therefore, blocking ACE reduces these effects and lowers pressure and cardiac workload.
Clinicians prescribe ACE inhibitors for hypertension, selected heart-failure patients, some kidney conditions, and certain patients after a heart attack. The benefits depend on the underlying diagnosis.
Bradykinin and sensitive airway nerves
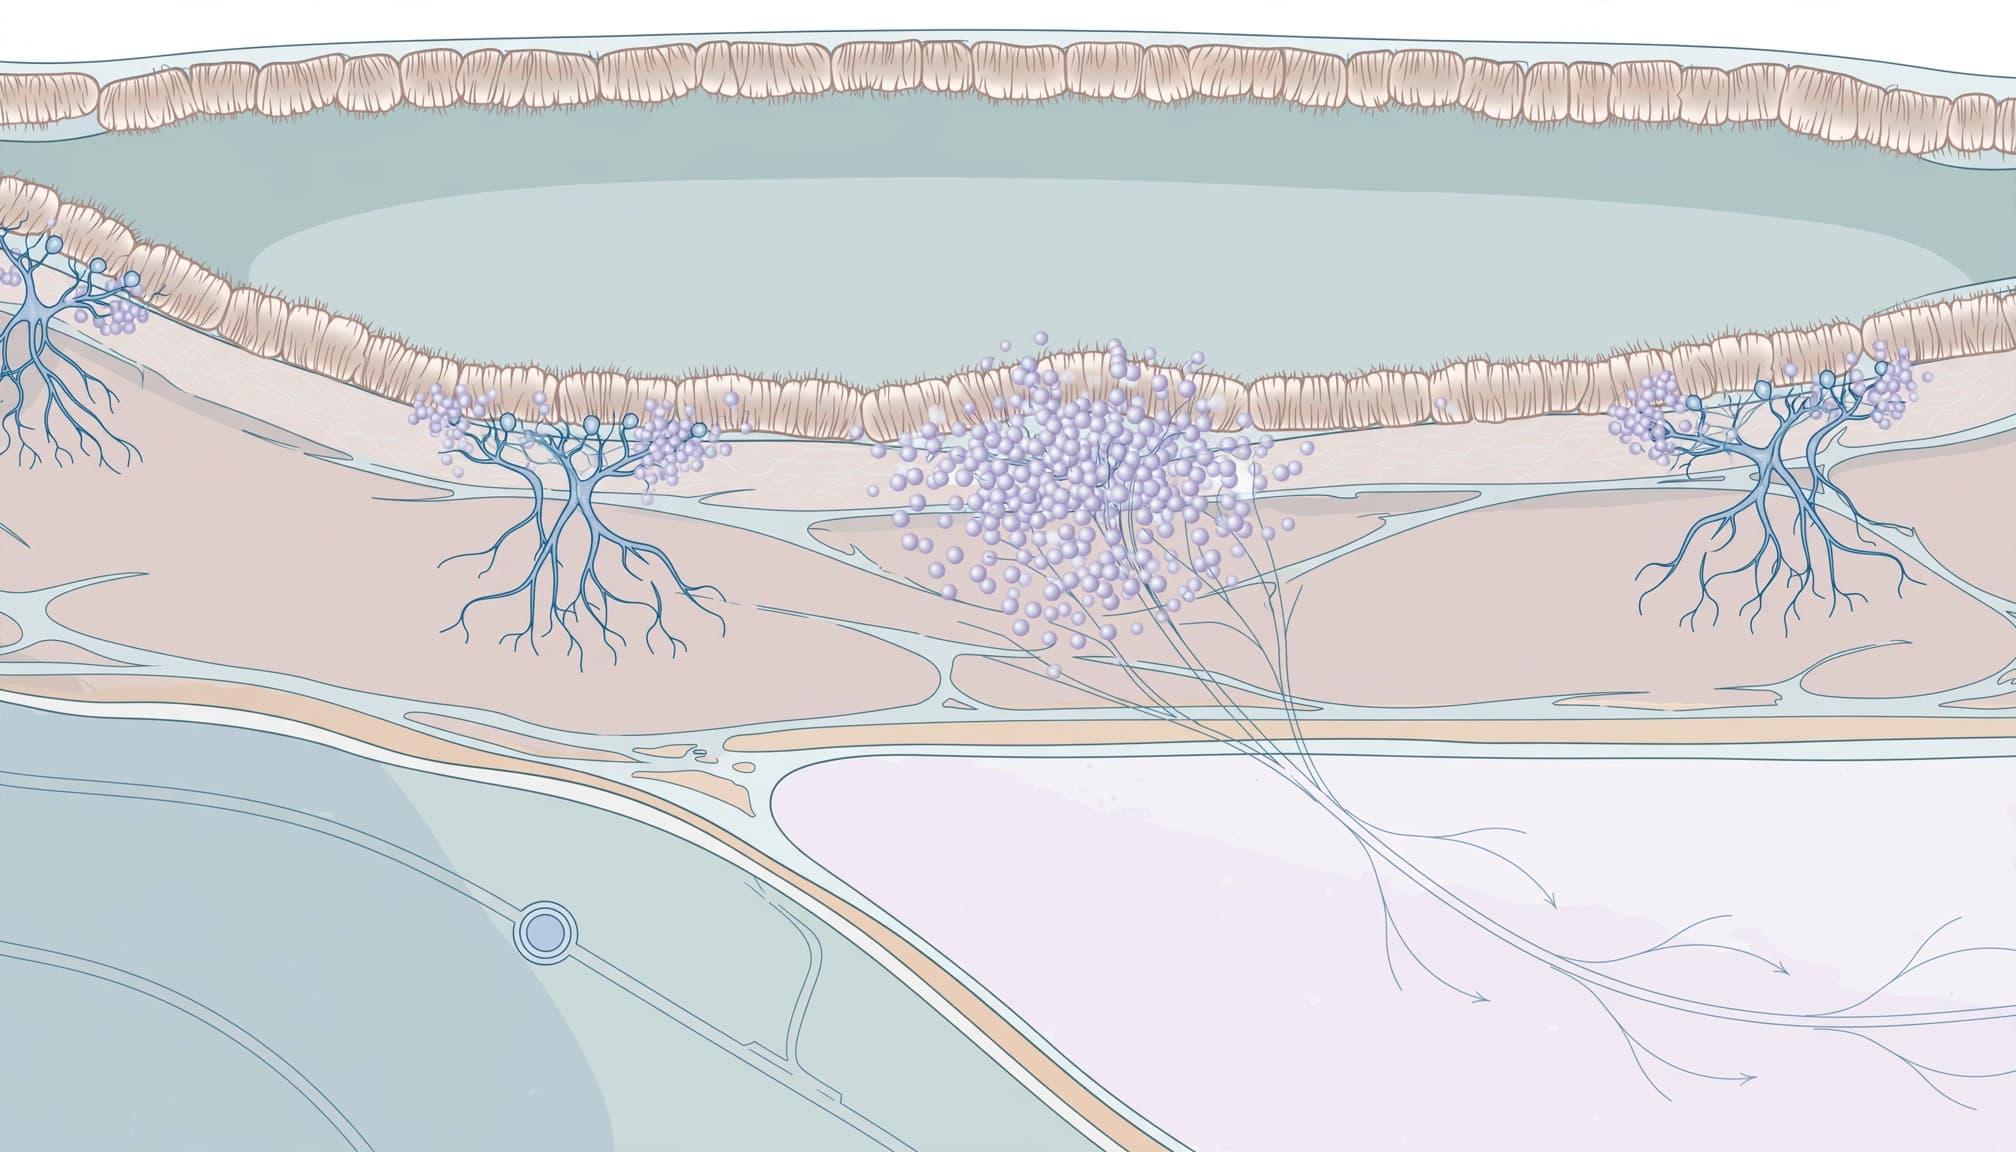
ACE also breaks down bradykinin and substance P. When treatment blocks the enzyme, bradykinin and substance P can accumulate and stimulate sensory nerves in the airways.
Peter Dicpinigaitis' ACCP evidence-based cough guideline describes this mechanism. The airway becomes more sensitive to triggers, so a small irritation can heighten the cough reflex without producing mucus.
ACE inhibitor cough generally isn't dose-dependent. It can occur at a low dose, so reducing the tablet strength doesn't reliably solve the problem.
Recognizing the cough and its timing
A dry, tickly pattern
ACE inhibitor cough is typically non-productive, meaning it brings up little or no mucus. Patients often describe an itchy throat or a recurring tickle that starts another coughing spell.
It can be worse at night or when lying down. However, those features also occur with reflux, asthma, and nasal drainage, so they don't establish the diagnosis alone. Sleep disruption can be substantial even when examination findings are normal.

Frequency and delayed onset
About one in ten patients develops this side effect. Estimates commonly fall around 5% to 20%, although some studies report wider ranges because populations and methods differ.
Women have roughly twice the reported risk in some studies. The cough can begin within the first week or appear after six months. Therefore, a recent prescription change isn't necessary for medication-related coughing to remain a possibility.
Which medicines can cause the cough?
ACE inhibitors have generic names ending in -pril. They include ramipril, perindopril, lisinopril, enalapril, quinapril, captopril, trandolapril, and fosinopril.
Our lisinopril medication information describes one commonly prescribed example. This medicine, also sold as Altace, belongs to the same class; our medication safety information covers its precautions.
Combination tablets can obscure the connection. For example, perindopril with amlodipine still contains an ACE inhibitor, even though its brand name doesn't end in "pril."
An angiotensin receptor blocker, or ARB, generally has a generic name ending in -sartan. Examples include candesartan, losartan, valsartan, irbesartan, and telmisartan. These medicines block angiotensin II at its receptor rather than blocking ACE. Because they don't inhibit bradykinin breakdown, they don't usually cause this characteristic cough.
Switching to an ARB safely
Replacing treatment without losing protection
Discuss switching medication with the prescriber, and don't discontinue ACE inhibitor treatment without first agreeing on a replacement plan. Blood pressure may rise or heart failure may worsen if effective therapy stops without a replacement. A planned replacement can preserve treatment prescribed after a heart attack.
A prescriber may select an angiotensin receptor blocker as an alternative. The NHS overview of irbesartan describes one medicine in this class. Selection depends on the original indication, kidney function, other medicines, and previous reactions. Switching to another ACE inhibitor, such as enalapril, may not prevent this class-related effect.
Cough suppressants, antihistamines, inhalers, and reflux medicines don't address bradykinin accumulation. They may treat another condition, but they aren't reliable treatments for ACE inhibitor cough.
Recovery and monitoring
Improvement usually follows a prescriber-directed switch, although it isn't always immediate.
| Time after ACE inhibitor withdrawal | What commonly happens |
|---|---|
| First few days | Cough may continue despite the medicine change. |
| Two to four weeks | Many patients notice substantial improvement or resolution. |
| Up to three months | A minority takes longer to recover fully. |
A lingering cough during the first week doesn't establish that the replacement has failed.
The NHS monitoring guidance addresses blood pressure, kidney function, and potassium surveillance. The prescriber may recheck blood pressure and these other measures within one to two weeks after starting or changing treatment, sometimes sooner for higher-risk patients.
Our guide to heart-failure medication safety checks also explains these checks. ACE inhibitors and ARBs shouldn't be combined. Sacubitril/valsartan, a separate heart-failure treatment, requires at least 36 hours after the last ACE inhibitor dose.
Other causes of a persistent dry cough
Medication review belongs early in the assessment of chronic cough, including when the examination is normal. However, it doesn't automatically replace chest imaging or lung-function testing when symptoms or clinical findings justify them.
Post-nasal drip associated with allergic rhinitis can irritate the throat. Antihistamines may help allergy symptoms, but they don't address the ACE-related mechanism. Reflux may provoke coughing after meals or when lying down. Cough-variant asthma can cause a cough without obvious wheezing.
Medicines beyond ACE inhibitors also matter. Beta-blocker eye drops, including timolol, can provoke bronchospasm in susceptible patients.
A cough that persists beyond three months after ACE inhibitor withdrawal generally needs reassessment. Mucus production, coughing blood, or breathlessness also calls for investigation rather than assuming the tablet explains everything.
When swelling or breathlessness needs emergency care
An ordinary ACE inhibitor cough doesn't cause swelling of the lips, tongue, or throat. Such swelling can indicate angioedema, an uncommon but potentially life-threatening reaction affecting well under 1% of patients.
Difficulty breathing or swallowing requires emergency services. The medicine should be stopped when angioedema is suspected, with immediate emergency assessment rather than waiting for a routine appointment. NHS ACE inhibitor safety guidance identifies this reaction as rare but life-threatening.
A previous ACE inhibitor-associated angioedema episode changes future prescribing decisions. It shouldn't be managed as though it were uncomplicated cough.
This information is for educational purposes only. Consult a licensed healthcare provider before changing prescription medicine.
Accessing replacement treatment affordably
Generic ACE inhibitors and ARBs can offer lower-cost treatment than branded versions, although insurance and local dispensing charges affect the final bill. A generic switch within the ACE inhibitor class, however, doesn't reliably eliminate a class-related cough.
One listed generic candesartan 8 mg pack containing 30 tablets costs US$17.64. That pack price isn't a quote for medicine delivery to the USA.
Comparisons between USA, UK, Australian, and internationally sourced prescriptions need equivalent strengths and quantities. Delivery charges, insurance coverage, and any required monitoring also affect the total cost. International sourcing doesn't remove destination-country import requirements.
For patients arranging online medicine home delivery, a valid prescription and continuity of supply matter more than a low advertised price. Through our Online Pharmacy, prescription review precedes dispensing. A replacement order should follow the prescriber's treatment plan, including the agreed start date.
Frequently asked questions
What does a lisinopril cough sound like?
A lisinopril-related cough often sounds like repeated dry coughing or throat-clearing, without the wet sound associated with mucus. However, there is no distinctive sound that confirms the cause. Clinicians consider the medicine history, accompanying symptoms, examination, and response to a supervised treatment change.
Can ramipril cough start after years of treatment?
Yes. A persistent cough can develop after several years on the same ramipril dose, even after an initially symptom-free period. That delay doesn't exclude a medicine-related cause. However, clinicians still assess other explanations, particularly when new respiratory symptoms accompany the cough.
Is another ACE inhibitor less likely to cause coughing?
Individual studies report differences, but a cough caused by one ACE inhibitor can recur with another because the medicines share the same mechanism. Changing to a different "pril" isn't a dependable solution. A prescriber may instead select an ARB or another suitable class.
Are ARBs suitable for everyone with this cough?
No. ARBs can raise potassium, alter kidney function, and cause low blood pressure. They aren't suitable during pregnancy. Previous angioedema also requires careful assessment. The choice depends on the patient's diagnosis and safety profile, rather than the presence of cough alone.
Does a dry cough mean the medicine is damaging the lungs?
A typical ACE inhibitor cough reflects heightened cough-reflex sensitivity rather than proof of structural lung damage. Nevertheless, that explanation shouldn't dismiss other symptoms. Fever, weight loss, chest pain, coughing blood, or increasing breathlessness can point to another condition and require clinical assessment.
A treatable side effect with an important safety boundary
ACE inhibitor cough can be persistent because airway sensitivity takes time to settle after the medicine is withdrawn. A planned replacement usually preserves cardiovascular treatment while allowing the cough to resolve.
The safety distinction remains important: uncomplicated dry coughing warrants a prescribing review. Swelling or breathing difficulty requires emergency care, while persistent or atypical symptoms deserve investigation beyond the medication list.